
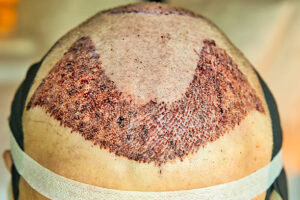

Genetic hair loss is one of the most common reasons people consider surgical restoration, but the treatment depends on more than simply replacing areas where hair has disappeared. For suitable candidates, Hair Transplant in Sharjah can restore genetically affected regions by redistributing permanent donor follicles while accounting for future progression, existing hair density, and the patient’s natural growth pattern.
Understanding Genetic Hair Loss
Genetic hair loss, commonly associated with androgenetic alopecia, develops through a combination of inherited follicular sensitivity and hormonal influence. The follicles most affected are generally located across the frontal scalp, temples, mid-scalp, and crown, while hairs in the donor region are often more resistant to progressive miniaturization.
How Follicular Miniaturization Changes the Scalp
A genetically susceptible follicle does not usually disappear immediately. Instead, successive growth cycles can produce progressively finer, shorter, and less pigmented hairs.
This miniaturization creates an important distinction during assessment. A scalp may appear substantially thinner even when some native follicles remain active. Those follicles need to be identified before transplantation so recipient sites can be created without unnecessarily damaging existing hair.
Genetic Pattern Matters During Planning
The distribution of loss provides information about how restoration should be approached. Some patients have predominantly frontal recession, while others develop diffuse thinning across several regions.
The pattern also helps determine whether surgical restoration should be concentrated in one area or distributed strategically. Treating every visibly thin region at the same time is not automatically the most appropriate use of a finite donor supply.
Why Donor Hair Is Central to Genetic Hair Loss Treatment
Hair transplantation is a redistribution procedure. It does not create additional follicles, which makes donor assessment one of the most important stages of treatment planning.
Evaluating Donor Density
The donor area is examined for follicular density, hair caliber, follicular-unit composition, scalp characteristics, and the stability of the region.
A donor zone containing many two-, three-, or four-hair follicular units can provide different coverage potential from a donor zone dominated by single-hair units. The surgeon therefore evaluates not only the number of available grafts but also what each graft can contribute visually.
Protecting the Future Donor Reserve
Genetic hair loss can continue after transplantation. A patient may therefore require a strategy that preserves enough donor follicles for possible future needs.
Aggressive extraction from the donor region can create visible depletion and reduce future flexibility. A measured plan considers the amount of grafts required now while maintaining the integrity of the donor area.
Donor Quality Versus Donor Quantity
A high graft count does not necessarily mean that a patient has unlimited restoration potential.
Hair diameter, follicular-unit composition, density, and the expected stability of the donor zone all influence the final planning decision. Two patients with similar visible baldness can therefore have very different surgical requirements.
How Recipient Areas Are Selected
Genetic hair loss does not affect every scalp region equally. Recipient planning should reflect the patient’s actual pattern rather than following a standardized template.
Frontal Restoration Requires Structural Precision
The frontal region establishes the transition between facial skin and scalp hair. Grafts placed here generally need to reproduce a fine, natural-looking arrangement rather than simply maximize density.
Single-hair follicular units can be particularly useful around the leading edge, while larger follicular units may be positioned farther behind where greater visual density is required.
Mid-Scalp Planning
Mid-scalp thinning can be challenging because native follicles may still be present throughout the area.
When transplantation is performed around existing hair, the placement angle and direction must correspond closely with the surrounding growth pattern. Poorly coordinated recipient sites can interfere with native follicles and create an artificial appearance.
Crown Treatment Requires a Different Strategy
The crown has its own directional pattern and frequently contains a whorl. It should therefore not be treated as though it were an extension of the frontal hairline.
For patients whose genetic loss includes the crown, graft allocation may need to account for the size of the affected area, existing density, the whorl pattern, and the possibility that crown loss could progress.
Choosing Grafts According to Genetic Hair Loss
The visual result depends heavily on how follicular units are distributed rather than simply how many are transplanted.
Single-Hair Units for Transition Zones
Fine single-hair grafts can help create a softer transition at exposed borders. Their placement is guided by the natural irregularity and direction of the patient’s existing hairline.
A perfectly straight or mechanically uniform arrangement can appear less natural because native hairlines rarely form a mathematically consistent edge.
Multi-Hair Units for Coverage
Two-, three-, and four-hair follicular units can provide greater visual coverage when positioned behind the transition zone.
Their distribution must remain compatible with the surrounding density. Concentrating larger grafts too close to the front can produce an overly heavy hairline, while scattering them without a density strategy can waste valuable donor resources.
Extraction and Graft Handling in Genetic Hair Loss Cases
The quality of the extracted graft remains important after the overall design has been established.
Accurate Follicular Extraction
During follicular unit extraction, the punch must be aligned appropriately with the follicle beneath the scalp. This becomes particularly relevant when follicles have different orientations or when the donor hair has curvature.
The objective is to obtain intact follicular units while minimizing unnecessary trauma to the surrounding tissue.
Protecting the Graft During Preparation
Extracted grafts are handled carefully before implantation. Follicular units contain structures that contribute to their survival and subsequent growth, so unnecessary manipulation should be avoided.
The grafts are then organized according to their composition and intended placement. This allows the surgical team to use the appropriate follicular units for different recipient zones.
Recipient-Site Direction
Recipient sites determine the angle and direction in which transplanted follicles will grow.
The frontal region may require a lower, forward-oriented angle, while the direction changes progressively toward the mid-scalp and crown. Matching these transitions helps transplanted follicles integrate with native hair.
When Genetic Hair Loss May Require More Than One Planning Stage
A genetically driven pattern can evolve over time. This makes long-term planning particularly important for younger patients or those with active progression.
Existing Native Hair Can Continue to Change
Transplanted follicles may remain stable while surrounding genetically susceptible native hairs continue to miniaturize.
This is one reason a conservative design can be preferable to filling every area aggressively during an initial procedure. The objective is to create a result that remains coherent as the surrounding scalp changes.
Stabilization Can Influence Timing
A clinical assessment may consider whether the patient’s pattern appears stable or whether substantial progression is still occurring.
Non-surgical hair-loss management may sometimes form part of an overall strategy alongside transplantation. The appropriate approach depends on the individual’s diagnosis, scalp condition, donor reserve, and progression pattern.
A Practical Genetic Hair Loss Assessment
Before surgery, several variables can be reviewed together rather than relying solely on the visible bald area.
| Assessment factor | Why it matters |
|---|---|
| Family pattern | Provides context for potential progression |
| Donor density | Indicates available follicular resources |
| Hair caliber | Influences visual coverage |
| Follicular-unit composition | Helps determine graft distribution |
| Miniaturization | Identifies vulnerable native hair |
| Scalp condition | Influences recipient-site planning |
| Loss pattern | Determines treatment priorities |
| Future progression | Supports long-term donor conservation |
This assessment prevents a common planning error: designing the procedure around today’s appearance without considering how genetically influenced loss may develop later.
How Genetic Hair Loss Differs From Temporary Shedding
Not every case of thinning should immediately be categorized as genetic hair loss.
Temporary shedding can occur for several reasons and may have a different clinical course from progressive follicular miniaturization. A proper assessment should distinguish between generalized shedding, localized thinning, miniaturization, and established areas of follicular loss.
This distinction matters because transplantation is intended for carefully selected areas where follicles require permanent redistribution. It is not simply a treatment for every episode of increased hair shedding.
Natural Integration After Hair Restoration
A successful restoration should not look like a separate layer of transplanted hair placed over the scalp. The transplanted follicles need to integrate visually with the patient’s existing hair.
Matching Hair Characteristics
Hair diameter, texture, curl pattern, growth direction, and follicular-unit composition can all influence how grafts blend with native hair.
A patient with fine hair may require a different density strategy from someone with thick shafts. Likewise, naturally curly or wavy hair can create additional visual coverage but requires careful consideration during extraction and implantation.
Preserving Native Hair
Recipient-site creation must account for the location of existing follicles.
When native hair remains within a thinning area, the surgical plan should work around those follicles rather than treating the scalp as completely empty. This becomes particularly important in diffuse genetic thinning, where visible loss may exceed the actual number of follicles that have been permanently lost.
What Patients Should Understand About the Result
Hair restoration does not immediately recreate mature terminal hair. Transplanted follicles go through a biological growth process, and the visible outcome develops gradually.
The early postoperative period is therefore different from the later maturation phase. New growth can initially appear fine before progressively developing greater caliber and visual presence.
The final appearance is influenced by donor characteristics, graft survival, recipient-site design, existing native hair, and the progression of untreated genetic loss.
Questions Patients Commonly Ask
Can genetic hair loss be treated with a transplant?
Yes, suitable areas can be restored using follicles harvested from a stable donor region. Candidate selection depends on the pattern and progression of hair loss and the available donor supply.
Does a transplant stop genetic hair loss?
No. Transplantation redistributes selected follicles but does not eliminate the underlying tendency for susceptible native follicles to miniaturize.
Can existing thinning hair be transplanted around?
Often, yes. When native follicles remain, recipient sites can be planned around them, provided the area and follicular condition are suitable for surgery.
Is donor hair permanently resistant to genetic loss?
Donor follicles are generally more resistant to androgenetic miniaturization, but individual donor stability must still be assessed clinically rather than assumed.
Can genetic hair loss return after transplantation?
Native hair surrounding the transplanted follicles can continue to thin. Long-term planning therefore needs to consider both transplanted follicles and the future behavior of native hair.
Planning Genetic Hair Restoration With Clinical Precision
Genetic hair loss is best approached as a long-term follicular planning problem rather than a simple attempt to fill visible bald patches. The key variables include donor stability, miniaturization, follicular-unit composition, recipient anatomy, hair characteristics, and the expected progression of the patient’s pattern.
For patients considering Tajmeels Clinic in Dubai, the assessment can focus on creating a restoration strategy that respects existing hair while using donor follicles efficiently. The objective is not merely to add grafts, but to establish appropriate density, direction, distribution, and long-term compatibility with the patient’s natural hair.
The Strategic Investment
A well-planned approach to genetic hair loss begins with understanding which follicles are likely to remain stable and which areas may continue to change. That distinction allows surgical planning to become more conservative and anatomically informed, particularly when donor resources need to support future restoration.
Patients exploring hair restoration can discuss their pattern, donor characteristics, and treatment goals with Tajmeels Clinic in Dubai to determine whether transplantation is appropriate for their individual presentation.


